Pain control is among those skills that defines the quality of frontline treatment. When a patient is twisting on the flooring of a manufacturing facility, or a child is panicked after a substance fracture at a weekend video game, you do not have long to make sound choices. PUAEME008, Provide Pain Administration, orders what competent -responders must do to examine discomfort, pick and provide safe analgesia, screen results, and turn over care. It is more than a device of expertise. It is a small between a medical professional and an individual in distress.
I have actually supplied and analyzed this device for mixed teams, from remote mine paramedics to urbane event paramedics, and the very same motifs turn up every program: know your pharmacology and contraindications, regard approval and regulation, always remember non‑pharmacological treatment, and paper as if another person will need to keep up the baton ten minutes later on. This short article unloads PUAEME008 in useful terms and offers a functioning picture of what proficient efficiency resembles in genuine environments.
Where PUAEME008 Sits in Practice
PUAEME008 sits in the general public Security Training Plan and is frequently packaged right into discomfort administration courses run by signed up training organisations for emergency -responders and allied health experts working in ascetic or prehospital contexts. Students are generally already learnt main study, air passage monitoring, fundamental life support, and scene safety and security. The provide pain monitoring program builds on that structure to deal with safe, effective analgesia throughout a range of individuals and environments.
Providers differ across Australia. Some deliver the device as a standalone pain management certificate course, others fold it into broader programs like remote location very first -responder training. For nurses and physiotherapists that work in event medicine, occupational wellness, or remote outreach, it can match specialist registration by formalising prehospital analgesia skills. It is not an alternative to a tertiary pain fellowship. Instead, it is a concentrated emergency pain monitoring component that asks a vital concern: can you ease discomfort rapidly and safely while expecting deterioration?
The Expertise at a Glance
PUAEME008 assessors look for clear, observable efficiency. The wording varies somewhat throughout versions, yet the core demands stay steady:
- Recognise and evaluate acute pain making use of structured tools matched to the client and situation. Select proper analgesic approaches, including non‑pharmacological approaches, according to protocols, range of practice, and available resources. Administer analgesia safely using authorized paths, dosages, and devices while maintaining infection control. Monitor reaction, unfavorable effects, and vital signs, after that titrate or stop therapy accordingly. Communicate clearly, gain consent, file, and hand over to a higher degree of care.
These elements audio tidy on paper. Genuine scenes are not. You will evaluate an individual with disruptive injuries and a wind blowing sand into your eyes. You will certainly look for a radial pulse while a group movies on their phones. Skills shows in just how you build a quick however trustworthy photo, keep the patient involved and tranquility, and apply a method without passage vision.
Assessment and Triage: Reading Pain, Not Presuming It
Pain is subjective and greatly coloured by fear, culture, and context. A jackaroo with a dislocated shoulder could rank his pain at six yet look light and clammy with a heart rate of 130. A child might decline to talk yet wince with a light touch. PUAEME008 expects responders to use pain ranges that fit the individual. The numeric rating scale from 0 to 10 matches articulate grownups. The Wong‑Baker encounters scale helps with interaction with youngsters or people that prefer aesthetic cues. For non‑verbal people, behavioral devices such as the FLACC range help, though they require practice to prevent overcalling distress as pain.

Acute discomfort evaluation in the area need to not drift into a lengthy meeting. Anchor it within the main and second surveys. Begin with life threats, then a concentrated discomfort background: area, beginning, personality, radiation, severity, time program, exacerbating or alleviating factors, and previous analgesics. Pulse oximetry, heart price, respiratory system price, high blood pressure, and skin indications offer context. Note warnings that change the strategy: transformed psychological state, suspected significant hemorrhage, upper body pain with hemodynamic instability, extreme head injury, or indications of sepsis. PUAEME008 wants responders to identify when analgesia is needed and when support of air passage, breathing, and circulation needs to precede it by minutes that really feel much longer.
Anecdotally, the most typical assessment error from new learners is falling short to reassess. They capture a standard discomfort rating, provide an opioid, then carry on with other jobs. Ten mins later the pain has actually held one's ground, but since no structured reassessment took place, the opportunity to titrate is lost. Great technique is simple. Tape-record a pain score before therapy, then again every 5 to 10 mins or after each dose. Pair it with vitals and an observation of sedation level, so you can identify breathing depression early.
Pharmacological Choices: What remains in the Kit and When to Make use of It
The provide pain administration course educates pharmacological choices lined up to organisational methods. Schedule differs. Remote centers might equip methoxyflurane, intranasal fentanyl, paracetamol, and advil. Occasion paramedics may operate under standing orders for dental anesthetics only. Paramedic solutions add IV morphine, ketamine, and sometimes nitrous oxide.
Paracetamol stays the quiet workhorse. At healing doses it lowers discomfort in bone and joint injuries and soft tissue injury. It additionally sets well with NSAIDs for a synergistic impact. Check for current intake to avoid cumulative poisoning, especially in smaller sized grownups or those with liver illness. Ibuprofen and various other NSAIDs bring anti‑inflammatory advantages yet carry bleeding and renal threats. Post‑operative clients, the elderly with inadequate kidney book, and people on anticoagulants could be much better served by different strategies.
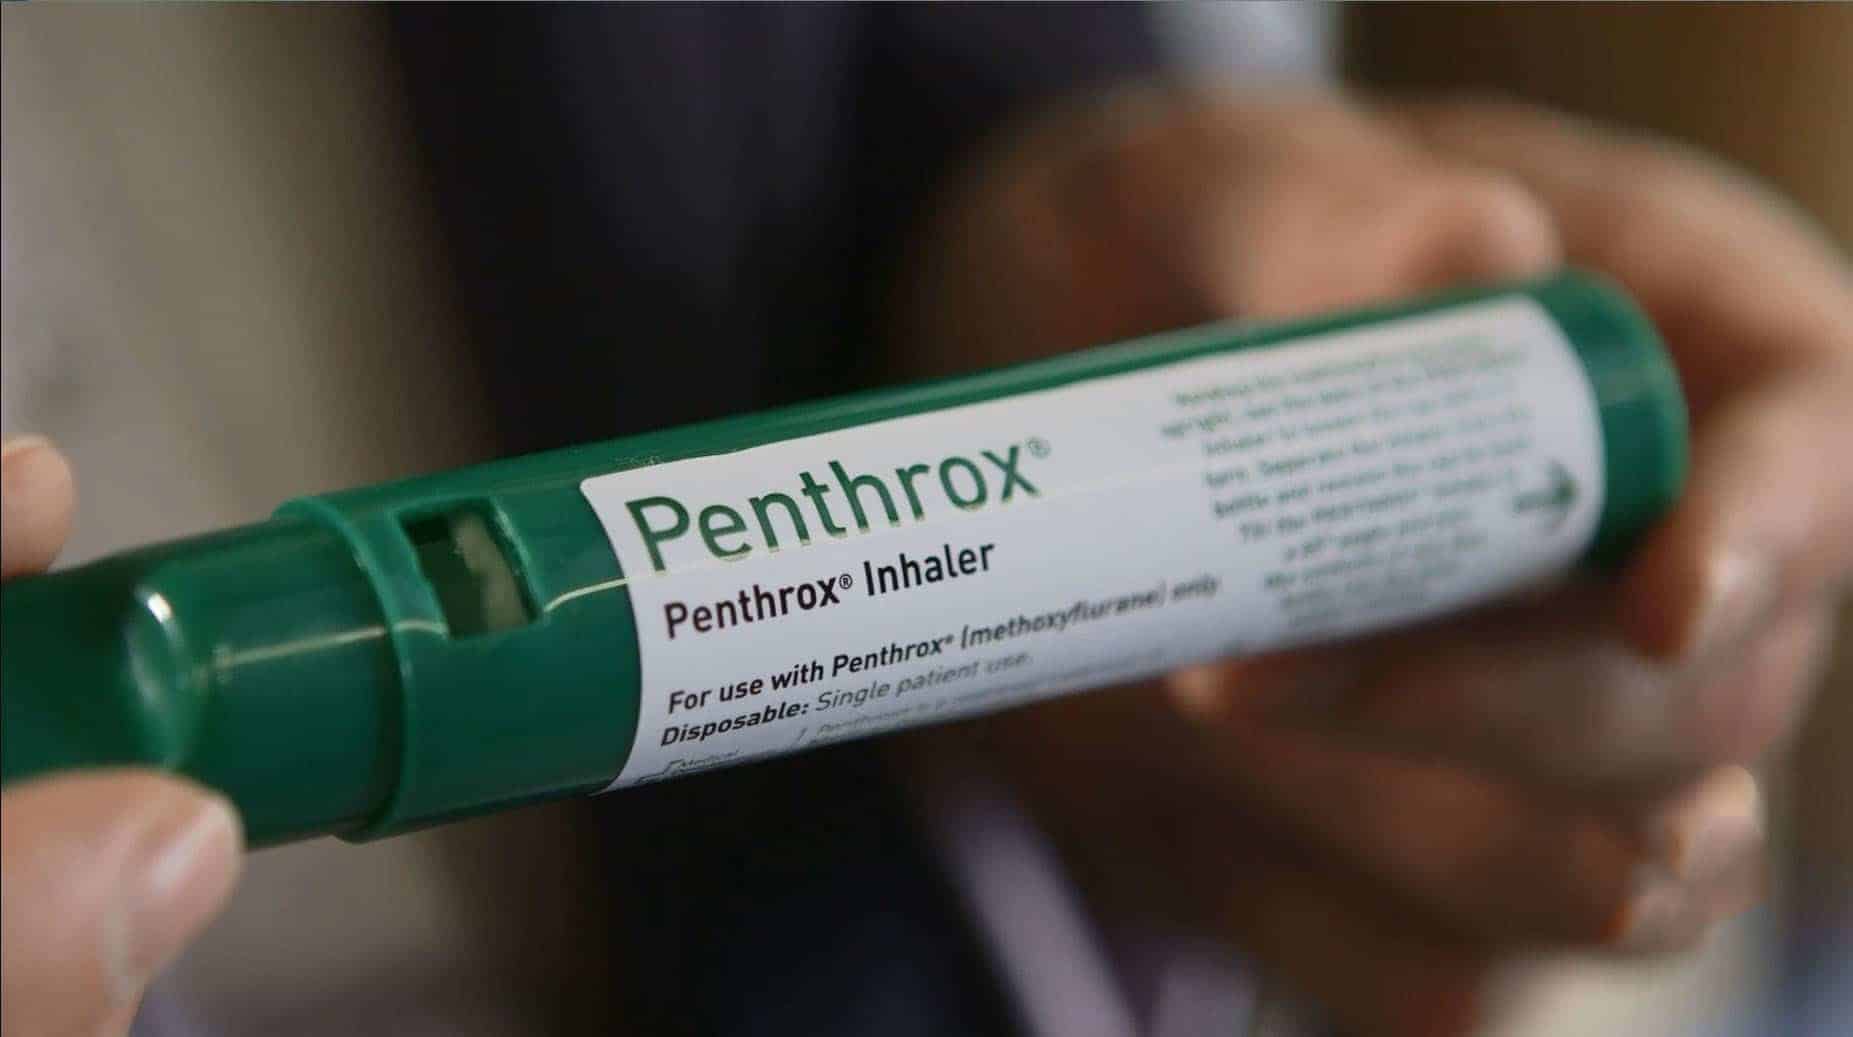
Methoxyflurane, provided through a handheld inhaler, has a loyal adhering to in the area. Its quick start and patient‑controlled nature fit short, painful treatments like decreasing a dislocated shoulder or splinting a crack. Look for sedation, hypotension, and the collective dosage restriction. Several procedures top it at 2 3 millilitre vials in 24 hr. I have actually had patients that hardly touched the inhaler after the first minute since concentrated coaching and splinting alleviated. Others needed the complete allowance to promote extrication. It is appealing to get along with strategies while the individual is calm, however if their vitals trend poorly, quit and reassess prior to continuing.
Intranasal fentanyl bridges a key void when IV gain access to is not possible. Right dosing based on patient weight and shipment using a mucosal atomisation device returns quickly analgesia. It is especially valuable in paediatrics where cannulation hold-ups treatment. Regardless of the comfort, treat it with the regard you would certainly any type of opioid. Know your contraindications, display respiration, and have naloxone prepared, drawn up, and close at hand. 2 percent of trainees fail to remember to prime the atomiser during simulations, which lowers effectiveness. Build a practice of a quick equipment list prior to administration.
IV opioids remain staples for many services. Titrated increments of morphine or fentanyl permit specific control. I choose tiny boluses connected to repeated pain scores and sedation analyses rather than huge front‑loaded dosages, specifically for older adults. Ketamine offers a dissociative route for serious pain, especially in injury where hypotension looms. Low dose ketamine for analgesia varies from induction doses made use of in procedural sedation. Nystagmus and dissociation can unsettle the patient and spectators, so extensive pre‑briefing helps. I have actually located that tranquil narration during management minimizes the possibility the patient will certainly stress as the medication takes effect.
Nitrous oxide still appears at some occasions. It is excellent for short, sharp procedures, however logistics and contraindications complicate its use. Expecting clients, those with bowel obstruction, pneumothorax, or trapped gas issues must not get it. Cylinder monitoring at a jampacked website ends up being a secondary danger otherwise controlled.
Whichever representatives you lug, PUAEME008 anchors method in clear procedures and extent. Do not improvise beyond training and authorisation, even when pressure mounts. If your discomfort monitoring training program covered intranasal pain management courses for nurses fentanyl and you work under a contract that allows it, you are on solid ground. If ketamine is not in your method design, the best option is to rise or seek additional assistance, not to push boundaries.
Non medicinal Methods: Usually Faster, Always Cheaper
I have enjoyed a nervous client's discomfort decrease from 8 to 4 within 2 mins with absolutely nothing more than an excellent splint, a warm blanket, and regulated breathing. We speak about medicines due to the fact that they feel like action, but foundational steps matter.
Immobilisation and splinting continue to be the most powerful non‑drug treatments for trauma discomfort. Correctly cushioned, well positioned splints reduce activity and muscular tissue spasm. Gentle grip in presumed lengthy bone cracks can eliminate the worst of it also before definitive treatment. Cold therapy decreases swelling and numbs superficial cells when made use of sensibly. Warmth can assist muscle spasm, yet avoid it on fresh distressing injuries.

Positioning slides under the radar. A client with kidney rock pain usually locates relief crinkled on one side. Rib cracks feel better with the chest somewhat raised and sustained. Encourage settings that minimize muscle mass pressure, provided spinal injury is not suspected. Basic breathing mentoring reduces considerate drive and raises tolerance. I utilize a 3 matter in, six pass over rhythm to advertise parasympathetic tone, tuned to the individual's convenience. Include disturbance. Assisted imagery appears soft till you see a kid with a lower arm crack resolve sufficient for cannulation since you asked about their canine and the following football match.
Non medicinal care is where physiotherapists pain management certificate course and registered nurses bring massive worth. Discomfort administration courses for physiotherapists commonly stress motion techniques that minimize pain without spiking anxiety, and nurses bring an intuition for positioning and confidence that pays returns. PUAEME008 anticipates responders to show these actions alongside pharmacology, not as a consolation prize when the medicine kit is light.
Consent, Interaction, and Social Safety
Consent can not be a rushed checkbox. Almost every area mistake I have actually examined after a damaging response included inadequate pre‑briefing. Before you deliver any type of analgesia, clarify what you intend to do, why, what the individual could feel, and what adverse effects to look for, then request for consent. Adults with capability can reject discomfort relief also if you think it is in their passion. Paper the conversation.
Cultural safety issues. Avoid presumptions concerning discomfort expression. Some patients will underreport pain to meet perceived expectations. Making use of neutral, open language assists. Rather than asking "Is it a 10 out of 10?", try "Can you reveal me on this scale just how solid the discomfort feels now?" For Very first Nations clients, welcome a support person when feasible and be mindful of gendered treatment preferences in some areas. Time invested earning trust is hardly ever lost and commonly shortens the total time to effective alleviation because the client engages with your plan.
Paediatrics and older grownups call for unique interest. With kids, consent involves parents or guardians, however the kid is worthy of an age‑appropriate description and assent. Older adults metabolise drugs differently, and polypharmacy increases threat. Halve the initial dosage, titrate gradually, and keep a hawk's eye on respiration. I have actually stood in lengthy transport lines up during heatwaves where a little second dose of an opioid tipped a frail client from comfortable to dangerously drowsy. Methods commonly enable half dosages for older adults. Usage that flexibility.
Monitoring and Handling Negative Effects
Monitoring is the spine of secure analgesia. Record standard vitals and repeat at periods fit to the medicine's onset and height. Opioids demand respiration rate and deepness checks, oxygen saturation fads, indicators of air passage blockage, and sedation level. Ketamine asks for blood pressure, heart rate, nystagmus monitoring, introduction reactions, and queasiness. Methoxyflurane requires focus to level of consciousness and blood pressure. Non‑opioid agents are not free passes. NSAIDs carry GI blood loss and renal stress danger, though these emerge over longer perspectives. Watch for allergy with any agent.
Adverse effects take place, despite perfect technique. The metric of competence is not preventing every event. It is acknowledgment and decisive management. If an individual ends up being excessively sedated after fentanyl, stop application, sustain the airway, use supplementary oxygen, and prepared bag‑valve‑mask support. If ventilation is poor or oxygen saturation falls in spite of respiratory tract maneuvers, make use of naloxone per protocol. I instruct pupils to pre‑calculate the naloxone dosage for their person immediately after providing an opioid, and to verbalise the area of the ampoule. Under anxiety, this small practice maintains your response measured instead of frantic.
Nausea is common, particularly with opioids and methoxyflurane. Have antiemetics available and position a vomit bag in the individual's hands. Lightheadedness and orthostatic drops in stress commonly fix with placing and fluids, if protocols permit. Watch on the clock. Drugs have half lives, and transport times can be deceptive. If you carry out analgesia right prior to handover, connect that explicitly so the obtaining medical professional comprehends the timing and can anticipate the following reassessment window.
Documentation and Handover: The Tale Should Travel
Good notes make you a much better medical professional. Poor ones deteriorate depend on and connection. For PUAEME008, documents indicates the pain assessment tool used and ratings in time, the medicines carried out with dosage, path, and time, the individual's action, adverse results and actions taken, consent discussions, and non‑pharmacological measures. It additionally indicates context: mechanism of injury, placement found, and any type of barriers or delays.
Handover take advantage of a straightforward framework. I favour an adjusted IMIST‑AMBO approach for discomfort: Recognition, Device, Injuries/illness, Indications consisting of pain scores and vitals, Therapy offered (both non‑pharm and medicinal), and feedback. If the receiving team hears that you titrated 20 micrograms of intranasal fentanyl to a paediatric lower arm fracture, with pain reducing from eight to three, which the youngster continued to be alert with secure vitals and no nausea, they immediately recognize where to select up.
Training Pathways and Who Benefits
Pain management training can be found in various flavours. Short programs suffering monitoring packaged around PUAEME008 normally run 1 to 2 days, with a balance of theory, simulation, and useful evaluation. Some providers add optional modules like laughing gas handling, or advanced splinting. A certification program hurting monitoring at this level does not approve prescriptive authority by itself. It confirms skills to deliver analgesia within an organisation's scientific governance and standing orders.
For registered nurses who get changes in occasion medicine or run in country centers, pain administration training courses for registered nurses aid convert hospital‑based abilities right into prehospital restraints. Focus falls on limited resources, solo choice production, and paperwork that creases efficiently right into ambulance or retrieval handover. Physiotherapists working pitch‑side or in remote outreach add worth with biomechanics and mild motion approaches. Pain management courses for physiotherapists educate exactly how to combine those strengths with risk-free analgesic procedures when medical professionals are not promptly available.
Paramedic pupils usually encounter PUAEME008 integrated into their wider program. For very first responders in the sources sector, a supply pain administration program might be a licensing need prior to being rostered to solo insurance coverage. The pragmatic payback is clear. When I compare event reports prior to and after staff complete a discomfort management qualification training course, I constantly see faster time to very first analgesia and fewer unintended negative occasions. The act of exercising approval scripts, rehearsing application, and memorising red flags changes behavior under stress.
Equipment and Setting: Details That Matter
You do not need a healthcare facility to deliver excellent discomfort care, however you do require reputable set and a system that keeps it all set. Supply lists conserve jobs. Inhalers ran out last month assistance nobody. Atomisers that do not fit your syringes hinder strategies. Add human factors. A dim arena tunnel without a headlamp turns creating medicine right into a dangerous video game. A gusty roadside strips warmth from a semi‑dressed patient and pushes their discomfort up while you prepare a line. Little touches obtain ignored up until they bite. I put a thermal blanket under and over injury people whenever feasible, then reassess pain prior to I reach for drugs.
Storage and safety issue. Opioids need secured storage and mindful bookkeeping. Maintain a tamper‑evident system and train every personnel to utilize it similarly. Naloxone ought to sit near opioids, not hidden in a separate bag. I have actually seen teams keep it in an anaphylaxis package two zips away from the fentanyl. During a crisis, those zips come to be canyons.
Finally, rehearse where you stand. In confined transforming spaces, decide ahead of time who draws, who holds, that documents. Simulation with complete equipment deserves an hour of slides. The very first time you attempt to titrate ketamine while a striker's close friends crowd the entrance must not be the first time you understand your monitor cord is as well short for that corner.
Legal and Moral Boundaries
PUAEME008 assumes method within an administration framework. Administrative policies and organisational methods specify which agents you can make use of, under what conditions, and with what oversight. Pain management certification does not accredit you to experiment. It validates you can apply a defined procedure securely. Maintain copies of your extent of method, standing medication orders, and unfavorable event acceleration path available. If you work throughout organisations, expect variant. One company might allow intranasal fentanyl under a clinical practice standard. One more may limit your analgesia to dental agents and methoxyflurane.
Ethics surface most sharply when patients decline treatment, when bystanders push you to rush, or when an associate urges a shortcut that sneaks beyond method. Your anchor is the combination of patient autonomy, notified permission, and non‑maleficence. Decline to administer a medicine if contraindications exist, also if the patient firmly insists. On the other hand, do not hold back analgesia as a bargaining chip for participation. Straighten with the getting service early when you anticipate complex choices. A quick phone get in touch with buys scientific and legal cover.
Building Capability: What Quality Training Looks Like
Not all pain administration training courses cover the exact same ground. Search for programs that balance pharmacology with circumstance time, include equipment handling drills, and require demo of permission conversations. A good give discomfort administration program consists of:
- Realistic simulations that test evaluation, medication prep work, surveillance, and handover with time pressure. Coverage of non‑pharmacological methods alongside pharmacology, with functional splinting drills. Clear links to protocols and range, consisting of documentation templates and damaging occasion management. Paediatric and older adult considerations, with application variations and interaction techniques. Assessment that consists of repeated reassessments over a scenario, not simply a single dose and done.
As an assessor, I expect the rhythm of care: assess, decide, describe, prepare, provide, check, reassess, paper, hand over. When students internalise that loophole, their individuals improve care and their stress goes down.
Common Mistakes and Just how to Prevent Them
A couple of patterns appear consistently. The first is dealing with pain ratings as design as opposed to as choice supports. If the discomfort continues to be high after a sensible beginning duration and there are no unfavorable signs, titrate. If the discomfort goes down to a mild level, pivot to comfort measures and discontinue dosing. The second is tools errors: vacant atomisers, ran out vials, missing out on filters for inhalers. A pre‑shift list protects against the majority of these. The 3rd is ignoring non‑drug choices. Pain administration is not a competition to see just how quickly you can formulate fentanyl. Splint early, instructor breathing, regulate the environment, after that grab the vial.
The most significant risk is poor tracking. A patient who looks "comfortable enough" can still move right into respiratory system clinical depression, particularly in hot, encased rooms or during transport when motion wanes them. Construct habits that endure disturbance. Introduce your review breaks loud. Ask a colleague to establish a timer on the monitor or phone. Create administration times on your handwear cover if you must.
The Payoff: Faster Alleviation, Safer Treatment, Better Handover
When groups embrace the complete extent of PUAEME008, scenes feel various. Individuals move from panic to participation. Extrication times shrink since motion hurts less. Transportation is calmer, handovers more clear. In audits, you will see less outliers in application and a smoother spread of discomfort ratings trending down within 10 to 15 mins of first contact for modest trauma. The most effective compliment I have gotten after a hectic celebration shift originated from a getting nurse: "Your notes tell the story, and the person resembles the notes review."
If you are picking a discomfort monitoring certification training course, concentrate on programs that practice the tale from first call to handover as opposed to those that just show just how to push a drug. If you manage a group, installed the device right into normal skills upkeep. Pain management training for registered nurses, physiotherapists, and very first responders is not a one‑and‑done. Procedures evolve and abilities boring without usage. Quarterly brief drills keep the edge.
The heart of PUAEME008 is simple. Meet pain promptly and pleasantly, choose interventions that match the individual and the circumstance, watch very carefully, and inform the following clinician specifically what occurred. Do those points well and you will meet the expertise. Extra notably, you will certainly help people really feel risk-free once again in mins that or else extend into an eternity.